
TL;DR (for busy researchers):
-
HSV encephalitis: CSF PCR is the diagnostic workhorse (≈96–99% Se/Sp). Serology is late and low-yield.
-
Arboviral encephalitides (e.g., JEV, WNV, TBE): IgM ELISA (MAC-ELISA) is first-line; PCR has low yield once neurologic signs start; rapid antibody tests (RDTs) vary by brand/virus and need confirmation.
-
Confirmatory testing: Use PRNT when cross-reactivity is likely (flaviviruses, vaccination).

Why the assay type matters: target, matrix, and timing
-
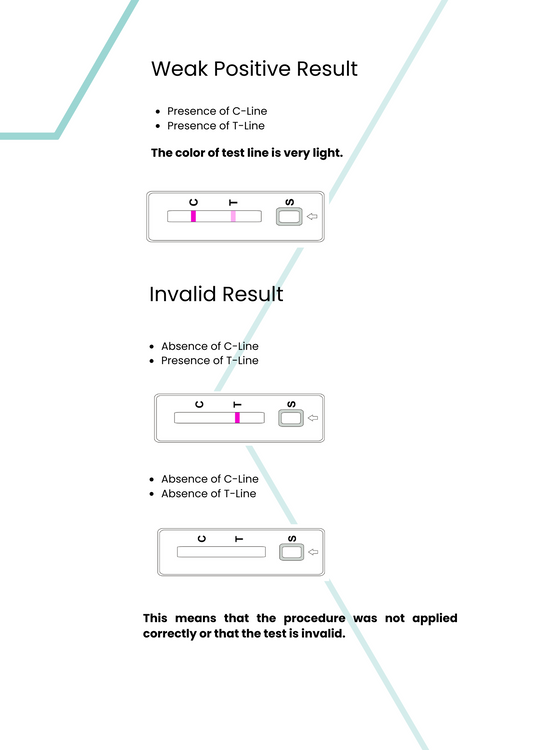
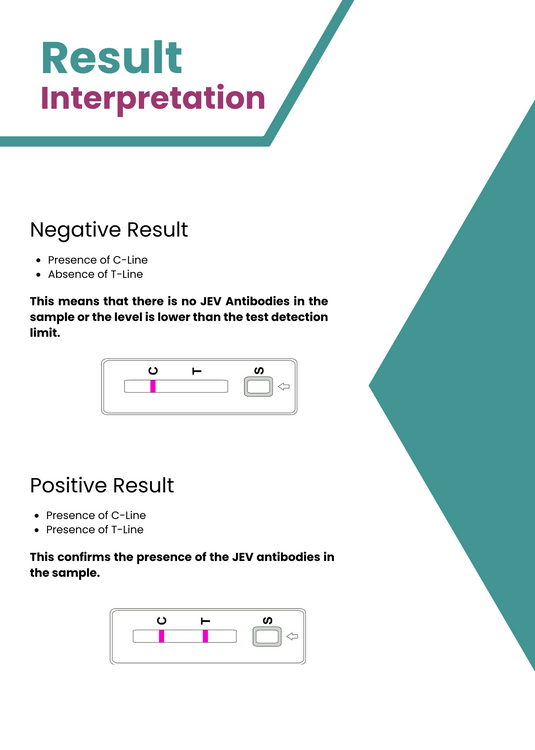
Rapid antibody tests (RDTs; lateral flow/dot formats) detect virus-specific IgM/IgG from serum/CSF in minutes. They are operationally simple but often trade analytical sensitivity and specificity for speed. Performance varies widely by manufacturer and virus family, and positives frequently require confirmation. See examples below.
-
ELISA (e.g., IgM MAC-ELISA) is the reference screening method in most arboviral encephalitis algorithms. It offers higher sensitivity than many RDTs and scalable throughput, but remains subject to flavivirus cross-reactivity, necessitating PRNT confirmation in many contexts. CDC WNV guidance, CDC JEV guidance. CDC+1
-
PCR/RT-PCR targets viral nucleic acid and is optimal early (before intrathecal antibody rises). For HSV encephalitis, CSF PCR is highly sensitive/specific and remains the frontline test. For arboviruses causing encephalitis, viremia/CSF viral RNA is typically low/brief by the time neurologic symptoms appear—limiting PCR yield except in special populations (e.g., the severely immunocompromised). NCBI Bookshelf—HSV, CDC WNV, CDC Yellow Book—TBE. Centre biotechnologieCDC+1
Head-to-head: sensitivity/specificity by pathogen group
1) Herpes Simplex Virus (HSV) encephalitis
-
PCR on CSF: sensitivity ≈96%, specificity ≈99% in immunocompetent adults; repeat testing is recommended if early sampling (<72 h) is negative but clinical suspicion is high. NCBI Bookshelf—StatPearls; corroborated by clinical series. UCLA, Case Western. Centre biotechnologieproceedings.med.ucla.eduCase Western Reserve University
-
Serology (IgM/IgG) in serum: generally not diagnostic for acute HSV encephalitis due to background seropositivity; intrathecal antibody may help late or when LP must be deferred. NCBI Bookshelf. Centre biotechnologie
-
University test pages (assay characteristics and matrices): Yale—PCR menus; OHSU—HSV1/2 PCR test details; Yale—HSV PCR performance brief. medicine.yale.eduknightdxlabs.ohsu.edufiles-profile.medicine.yale.edu
Conclusion for HSV: PCR outperforms antibody assays for sensitivity and specificity in real-time clinical decision-making.
2) Flaviviral encephalitis—Japanese Encephalitis virus (JEV)
-
ELISA (IgM MAC-ELISA): Primary diagnostic method; IgM detectable ~3–8 days after onset and can persist 30–90+ days. Sensitivity is high, including ~90% CSF detection by day 4, but specificity can be limited by cross-reactive flavivirus antibodies; confirm with PRNT when epidemiologically indicated. CDC JEV; Differential diagnosis of JEV—PMC. CDCPMC
-
PCR: Often insensitive at neurologic presentation due to low/undetectable viremia; not suitable to rule out JEV encephalitis. CDC JEV. CDC
-
Rapid antibody tests (RDTs): Performance varies. Early dot-immunoassay formats showed encouraging agreement in some settings, but several immunochromatographic RDTs have demonstrated poor sensitivity/specificity, necessitating ELISA/PRNT confirmation. MAC-DOT rapid JE—PMC; Poor performance of two JEV RDTs—PMC. PMC+1
3) West Nile virus (WNV) neuroinvasive disease
-
ELISA (IgM): CDC recommends IgM testing on serum and/or CSF; IgM appears 3–8 days after onset and may persist 30–90+ days; confirmatory PRNT helps adjudicate cross-reactivity. FDA 510(k) summaries for cleared IgM ELISAs report clinical sensitivities ~96–99% and specificities ~98–100% vs. PRNT/CDC methods. CDC WNV testing; FDA K041817. CDCFDA Access Data
-
PCR/RT-PCR: Low positivity in immunocompetent patients by the time neuroinvasive disease is recognized; consider in immunocompromised hosts with prolonged viremia. CDC WNV. CDC
-
Academic test references (interpretation nuances): UW test guide; Yale Lab Medicine menus. dlmp.uw.edumedicine.yale.edu
Conclusion for WNV: IgM ELISA is the highest-value initial assay; PCR is supplementary in select hosts; RDTs require careful validation and confirmation.
4) Tick-borne encephalitis virus (TBEV)
-
ELISA (IgM): Primary diagnostic test; cross-reactivity with other flaviviruses occurs; neutralization assays confirm. CDC TBE diagnosis. CDC
-
PCR: Not routinely recommended once neurologic phase begins; may be considered early or in immunocompromised hosts. CDC Yellow Book—TBE. CDC
-
Rapid antibody tests (RDTs): Some IgM rapid tests (e.g., ReaScan) have shown high sensitivity/specificity in multi-center evaluations (reported ~94–99% Se and ~98% Sp), but performance is assay-dependent and still benefits from confirmatory testing. Multi-lab evaluation—PMC; 2024 clinical evaluation—PMC. PMC+1
Comparative snapshot (typical clinical context)
| Use case | Best initial assay | Typical performance notes | Confirmation |
|---|---|---|---|
| HSV encephalitis (adult) | CSF PCR | ≈96–99% Se/Sp; repeat if very early and negative | — |
| JEV/WNV/TBEV (neuroinvasive) | IgM MAC-ELISA (serum ± CSF) | Good sensitivity after day 3–8; cross-reactivity can lower specificity | PRNT |
| Arboviral PCR | Early acute/immunocompromised | Often low sensitivity at neurologic phase | Use serology/PRNT |
| Antibody RDTs | Triage in field settings | Highly variable across brands/viruses; some excellent (TBE), others poor (some JEV kits) | Retest by ELISA ± PRNT |
Sources: CDC JEV; CDC WNV; CDC TBE; NCBI Bookshelf—HSV; FDA WNV ELISA 510(k); RDT evaluations. CDC+2CDC+2Centre biotechnologieFDA Access DataPMC
Practical algorithm (specimen-first, matrix-aware)
-
Suspected HSV encephalitis (temporal lobe syndrome, acute febrile encephalopathy): CSF HSV-1/2 PCR immediately; if initial test <72 h from onset is negative but suspicion is high, continue acyclovir and repeat PCR in 3–7 days. NCBI Bookshelf. Centre biotechnologie
-
Suspected flaviviral neuroinvasive disease (exposure geography/season consistent):
-
Send IgM MAC-ELISA on serum ± CSF.
-
If positive—or if cross-reactivity/vaccination is plausible—send PRNT via public health lab/CDC. Consider PCR only very early or in immunocompromised hosts. CDC WNV; CDC JEV; CDC Yellow Book—TBE. CDC+2CDC+2
-
-
Use of antibody RDTs:
-
Appropriate for triage/low-resource settings or urgent bedside screening.
-
Treat positive or equivocal RDTs as presumptive; confirm by ELISA ± PRNT. Performance is assay- and virus-specific (e.g., strong data for some TBE RDTs; mixed/poor for some JEV kits). ReaScan TBE studies; JEV RDT evaluation. PMC+1
-
Methodological nuances that drive Se/Sp
-
Windowing & kinetics: Arboviral IgM rises after viremia wanes; therefore PCR sensitivity drops when encephalitic symptoms commence, while IgM ELISA sensitivity climbs. CDC WNV; CDC JEV. CDC+1
-
Cross-reactivity: Flavivirus antigenic similarity reduces ELISA/RDT specificity, especially in vaccinated or previously infected populations; PRNT helps resolve true positives. CDC WNV; JEV differential—PMC. CDCPMC
-
Assay validation: FDA summaries for WNV IgM ELISAs report ≈96–99% sensitivity and 98–100% specificity vs. PRNT—benchmarks that many RDTs do not consistently meet. FDA K041817. FDA Access Data
-
Panel approaches: For undifferentiated encephalitis, multiplex CSF PCR panels may expedite early pathogen detection (including HSV/HHV6/enteroviruses), while arboviral serology proceeds in parallel. UNMC meningitis/encephalitis panel. unmc.edu
-
Yale Lab Medicine—seasonal/epidemic virology menu (notes that WNV is rarely PCR). medicine.yale.edu
-
OHSU—HSV1/2 PCR test details & matrices. knightdxlabs.ohsu.edu
-
CDC—JEV clinical diagnosis page (timing, PCR limits, PRNT). CDC
-
NCBI Bookshelf—HSV encephalitis overview and PCR performance. Centre biotechnologie
-
FDA 510(k) example—WNV IgM ELISA performance data. FDA Access Data
-
RDT performance—TBE (strong) vs. RDT performance—JEV (weak in some kits). PMC+1
-
Primary keywords: encephalitis virus antibody rapid test, IgM MAC-ELISA, PCR for encephalitis, sensitivity and specificity, Japanese encephalitis, West Nile virus, tick-borne encephalitis, PRNT confirmation.
-
Secondary: CSF PCR, serology cross-reactivity, diagnostic algorithm, lateral flow immunoassay, neuroinvasive disease diagnostics.
Key citations used throughout (selection)
CDC JEV testing; CDC WNV testing; CDC TBE (Yellow Book & clinician page); NCBI Bookshelf (HSV PCR Se/Sp); FDA 510(k) for WNV IgM ELISA; multi-lab evaluations of TBE IgM RDTs; JEV RDT performance papers; general PCR principles in viral encephalitis. CDC+3CDC+3CDC+3Centre biotechnologieFDA Access DataPMC+3PMC+3PMC+3


